


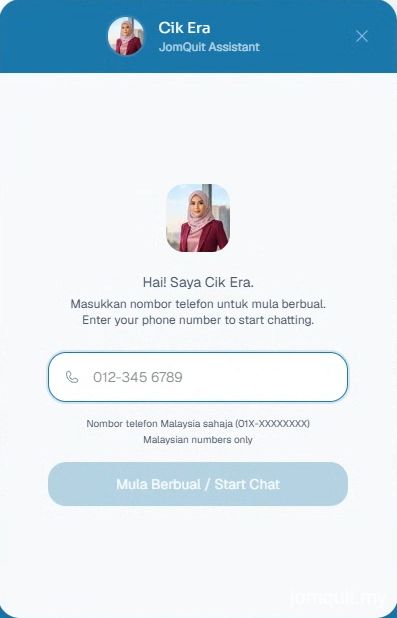
(Aug 28): Health Minister Datuk Seri Dr Dzulkefly Ahmad recently unveiled Cik Era, an artificial intelligence (AI)-powered chatbot designed to provide smokers and vapers with personalised, round-the-clock support as they attempt to quit. It is one of the Malaysian government's earliest efforts to deploy generative AI as a frontline public health intervention. More importantly, it invites the broader question: Can AI meaningfully expand access to healthcare while containing long-term costs? The answer will not only shape the future of smoking cessation services but the broader trajectory of digital healthcare in Malaysia.
Malaysia's tobacco burden remains stubbornly high despite decades of conventional control measures. The 2023 Global Adult Tobacco Survey estimated national smoking prevalence at 19%, with more than one in three men smoking compared with only about 1.5% of women, while tobacco use remains concentrated among adults aged between 25 and 44, the self-employed and those with only primary or secondary education.
The next generation, meanwhile, is taking up nicotine in a different form. The National Health and Morbidity Survey found that vaping among adolescents aged 13 to 17 rose from 9.8% in 2017 to 14.9% in 2022, including nearly one in four boys, even as teenage cigarette smoking declined to 6.2%. At the same time, the products themselves have become more dangerous. Police seizures earlier this year uncovering e-cigarette liquids adulterated with synthetic drugs such as methamphetamine, including a Johor laboratory producing narcotic-laced cartridges worth RM16.4 million. Tobacco control is no longer only to reduce cigarette consumption, but to manage a nicotine market that increasingly overlaps with the illicit drug trade.
Smoking costs Malaysia approximately RM11 billion every year. The government’s figure comprises RM6.2 billion in direct healthcare spending and about RM5 billion in losses associated with the illicit cigarette trade, against tobacco tax revenue of less than RM3 billion annually. Smoking-related illnesses also claim roughly 27,000 lives each year and earlier economic modelling estimated lifetime productivity losses among Malaysia's working-age male population at as much as RM275 billion. Against liabilities of this scale, an AI chatbot represents a comparatively modest investment if it can increase quit rates, reduce disease burden and delay the need for costlier care later.
Smoking cessation chatbots are not new. The Philippines has operated SMS quitlines since 2017, Thailand has introduced smartphone-based cessation applications and the World Health Organization runs its own chatbot, Sarah. What has changed is the arrival of large language models which enable conversational systems to provide more personalised support, sustain longer interactions and respond to users with a level of flexibility that earlier rule-based chatbots could not achieve. Malaysia's own experience appears to reflect this potential, with Cik Era recording more than 17,400 interactions since March and user engagement increasing substantially following its nationwide promotional campaign.
The emerging evidence is encouraging, if not yet definitive. A 2023 meta-analysis of five randomised controlled trials involving almost 59,000 participants found that conversational AI interventions improved six-month smoking cessation rates by 29% compared with no digital support. Systematic reviews have separately reported higher levels of motivation, confidence and sustained engagement than standard text-messaging programmes. For healthcare systems facing increasing demand but limited manpower, AI offers a way to extend the reach of trained healthcare professionals rather than replace them. The technology's greatest strength lies in its ability to provide immediate and continuous support to large numbers of users at relatively low marginal cost.
The same evidence carries a warning. One recent assessment of large language model-based smoking cessation chatbots, including the World Health Organization's Sarah, found that only 57% of responses fully complied with established public health guidelines, while misinformation appeared in 22% of responses. These findings illustrate an important distinction between conversational ability and clinical reliability, because an AI system that sounds persuasive does not necessarily provide consistently accurate advice. Before Cik Era is expanded further, it should undergo the same independent scrutiny expected of other healthcare interventions, including transparent assessments of clinical accuracy, guideline adherence and patient safety.
A further question is whether the programme is reaching the populations that need it most. Digital health initiatives often achieve their strongest uptake among urban, digitally connected users, yet the Global Adult Tobacco Survey shows that smoking remains disproportionately concentrated among self-employed workers, men with lower educational attainment and many rural communities. If Cik Era is to evolve beyond a successful pilot project, it must reach smokers through lower-bandwidth channels such as WhatsApp and SMS and be integrated with the community clinics, primary healthcare facilities and workplace health programmes that regularly engage higher-risk populations. Expanding accessibility will ultimately be as important as improving the underlying technology.
Quitting cigarettes and quitting vapes are no longer the same problem. The emergence of drug-adulterated vape liquids means vaping is not just another form of nicotine dependence, but in some instances a pathway to more serious substance-related harms that require different counselling strategies and referral mechanisms. Cik Era should therefore include a dedicated vaping cessation pathway that provides evidence-based advice and directs users who disclose potentially contaminated products to appropriate healthcare and support services through clear, non-judgmental escalation processes. Developing these safeguards will require careful policy design, but the ministry can no longer afford to treat vaping as merely an extension of conventional tobacco control.
None of these observations diminishes the value of the initiative. Instead, they define the standards by which it should now be assessed. The next stage should focus less on promotional campaigns and more on generating robust evidence through comparative quit-rate outcomes, independent audits of clinical accuracy and transparent reporting of how user data are collected, stored and protected. Such transparency would strengthen public confidence and ensure that innovation is accompanied by accountability, particularly in an area as sensitive as healthcare. Malaysia may not be the first country to introduce an AI-powered smoking cessation companion, but it can be among the first to publish rigorous local evidence demonstrating whether such a system produces meaningful improvements in real-world health outcomes.
AI will not eliminate nicotine addiction, nor should policymakers expect it to do so. Its greatest value lies in narrowing the gap between an individual's decision to quit and timely access to evidence-based support, particularly in healthcare systems where trained counsellors and specialist services remain limited. Cik Era represents a promising first step towards closing that gap, but its long-term success will ultimately depend less on the sophistication of the technology than on the quality of the evidence that supports it. If Malaysia intends to position AI as an integral part of its healthcare future, it must be equally committed to demonstrating that these technologies improve outcomes, earn public trust and deliver measurable value for every ringgit invested.
Dr David Chang, PhD, is a registered pharmacist. Lorraine Hoo is a registered pharmacist. Dr Sean Thum is a policy officer at the Ministry of Communications. Dr Wong Yen Jun is a lecturer at the School of Pharmacy, Monash University, Malaysia.